
Master Pranav, a 5-year-old male child, 2nd order child born of a non-consanguineous marriage to healthy parents from Hyderabad, Telangana, presented to the Pediatric Neurology & Neurogenetics Clinic with chief complaints of multiple, well-demarcated, hypopigmented lanceolate skin patches noticed over the trunk and extremities since early infancy, historical onset of epileptic flexor spasms in clusters (Infantile Spasms / West Syndrome) at 6 months of age successfully treated with oral Vigabatrin, emergence of reddish-pink, smooth, fleshy hamartomatous papules in a symmetrical butterfly distribution over the nose and cheeks (Facial Angiofibromas / Adenoma Sebaceum) for 1.5 years, a firm, cobblestone-like, leathery connective tissue plaque over the lumbosacral spine (Shagreen Patch), and mild cognitive delay with hyperactive behavior, whose comprehensive diagnostic evaluation demonstrated 8 Major Diagnostic Features of the 2021 International Tuberous Sclerosis Complex Consensus Criteria (including $>3$ Ash-leaf macules under Wood's lamp, facial angiofibromas, shagreen patch, multiple subependymal nodules, cortical tubers, retinal astrocytic hamartoma, cardiac rhabdomyoma, and an asymptomatic $1.2\text{ cm}$ subependymal giant cell astrocytoma at the Foramen of Monro), confirmed on molecular genetic testing to harbor a Heterozygous De Novo Pathogenic Mutation in the TSC2 Gene (Tuberin), diagnosed with Definitive Tuberous Sclerosis Complex (TSC), successfully managed with Levetiracetam seizure control, topical $0.1\%\text{ Sirolimus}$ Gel, and protocolized neuro-oncology surveillance for Everolimus (mTOR Inhibitor) therapy.
When examining a child with neurocutaneous stigmata and epilepsy, examiners expect a structured multi-organ synthesis:
- Dermatological Staging by Age of Appearance:
- Infancy: Hypomelanotic macules (Ash-leaf macules: polygonal lanceolate $>5\text{ mm}$, confetti macules); visible earliest under Wood's Lamp (UV light $365\text{ nm}$).
- Toddler / Early Childhood (3-5 years): Facial Angiofibromas (Adenoma sebaceum, butterfly malar distribution sparing upper lip) and Shagreen Patch (lumbosacral connective tissue nevus).
- Late Childhood / Adolescence: Periungual / Subungual fibromas (Koenen tumors).
- 2021 International Diagnostic Criteria:
- Definite Diagnosis: 2 Major Features OR 1 Major + $\ge 2$ Minor Features, OR identification of a pathogenic mutation in TSC1 or TSC2.
- The Neurological Spectrum:
- Infantile Spasms (West Syndrome): The classic presenting seizure; Vigabatrin (oral gamma-vinyl GABA) is the absolute drug of choice (superior to ACTH in TSC).
- Subependymal Giant Cell Astrocytoma (SEGA): Arises from SENs near the Foramen of Monro; monitor for hydrocephalus; treated medically with oral Everolimus (mTOR inhibitor).
- Cardiac Rhabdomyoma Natural History (Classic Viva Trap): Multiple ventricular rhabdomyomas detected in utero or infancy spontaneously regress during the first 2-3 years of life; surgery is contraindicated unless critical intracardiac outflow obstruction or refractory arrhythmia occurs!
Chief Complaints
- Multiple white, pale skin patches over the chest, abdomen, and thighs noticed since 2-3 months of age.
- History of sudden jerky bending movements of the body in clusters at 6 months of age (Infantile Spasms).
- Red pimple-like rash across the cheeks and bridge of the nose appearing over the past 1.5 years.
- Thick, leathery rough patch over the lower back noticed for 1 year.
- Restless, hyperactive behavior and mild learning difficulties.
HOPI
Master Pranav was born at full term following an uneventful pregnancy. At birth, mother noticed 2-3 faint, lanceolate pale patches on his back and left thigh, which were initially dismissed as birthmarks:
- Evolution of Cutaneous Hamartomas:
- By 6 months of age, the pale patches became more distinct: multiple, well-circumscribed, hypopigmented patches resembling mountain ash tree leaves (Ash-Leaf Macules) appeared across the trunk and thighs.
- Around 3.5 years of age, discrete, reddish-pink, smooth, glistening papules ($1-3\text{ mm}$) erupted over both cheeks and the bridge of the nose in a symmetrical butterfly distribution (Facial Angiofibromas / Adenoma Sebaceum), sparing the upper lip.
- A firm, yellowish-brown, thickened cobblestone plaque ($4 \times 3\text{ cm}$) appeared over the lumbosacral region around 4 years of age (Shagreen Patch).
- Multiple tiny ($1-2\text{ mm}$) stippled white spots noticed over the shins (Confetti Macules).
- No painful growths around the fingernails or toenails yet (periungual fibromas typically emerge after 8-10 years).
- Epilepsy & Neurodevelopmental Course:
- At 6 months of age, the infant developed sudden, repetitive paroxysms of flexion of the neck, abduction and forward elevation of both arms, and flexion of the thighs on the abdomen ('jackknife spasms').
- Spasms occurred in salvos of 15 to 30 episodes upon waking from sleep, accompanied by irritability.
- An electroencephalogram (EEG) performed at that time revealed classic Hypsarrhythmia (high-voltage, chaotic, disorganized background with multifocal sharp waves), confirming West Syndrome (Infantile Spasms).
- Evaluated and initiated on Vigabatrin ($100\text{ mg/kg/day}$), which resulted in complete cessation of spasms and resolution of hypsarrhythmia within 14 days.
- At 3 years of age, he transitioned to infrequent focal motor seizures with impaired awareness (lip smacking followed by right arm clonic jerking lasting 60 seconds), currently controlled on oral Levetiracetam ($30\text{ mg/kg/day}$).
- Cognitive trajectory: Speech milestones were mildly delayed (2-word phrases at 2.5 years); currently has a short attention span, hyperactivity, and sensory processing difficulties, fulfilling criteria for Tuberous Sclerosis-Associated Neuropsychiatric Disorder (TAND).
- Negative Inquiries:
- No severe early morning headaches, projectile vomiting, or lethargy (excludes acute obstructive hydrocephalus from SEGA).
- No gross hematuria, flank pain, or palpable abdominal masses (excludes large bleeding renal angiomyolipomas).
- No cyanosis, breathlessness, or heart failure symptoms (fetal echocardiogram was not performed, but infant never had congestive cardiac failure).
Past History
- History of West syndrome at 6 months treated with Vigabatrin for 12 months, weaned off without spasm recurrence.
- No history of status epilepticus, head trauma, or surgery.
Antenatal, Natal, and Developmental History
- Antenatal: Primigravida mother, uneventful; routine scans did not report cardiac masses.
- Natal: Full-term normal vaginal delivery; cried immediately; birth weight $3100\text{ grams}$.
- Developmental: Neck control at 4 months, sat at 9 months, walked at 16 months. Uses 3-word sentences; currently attending a specialized inclusive pre-school.
Family History
- Non-consanguineous marriage.
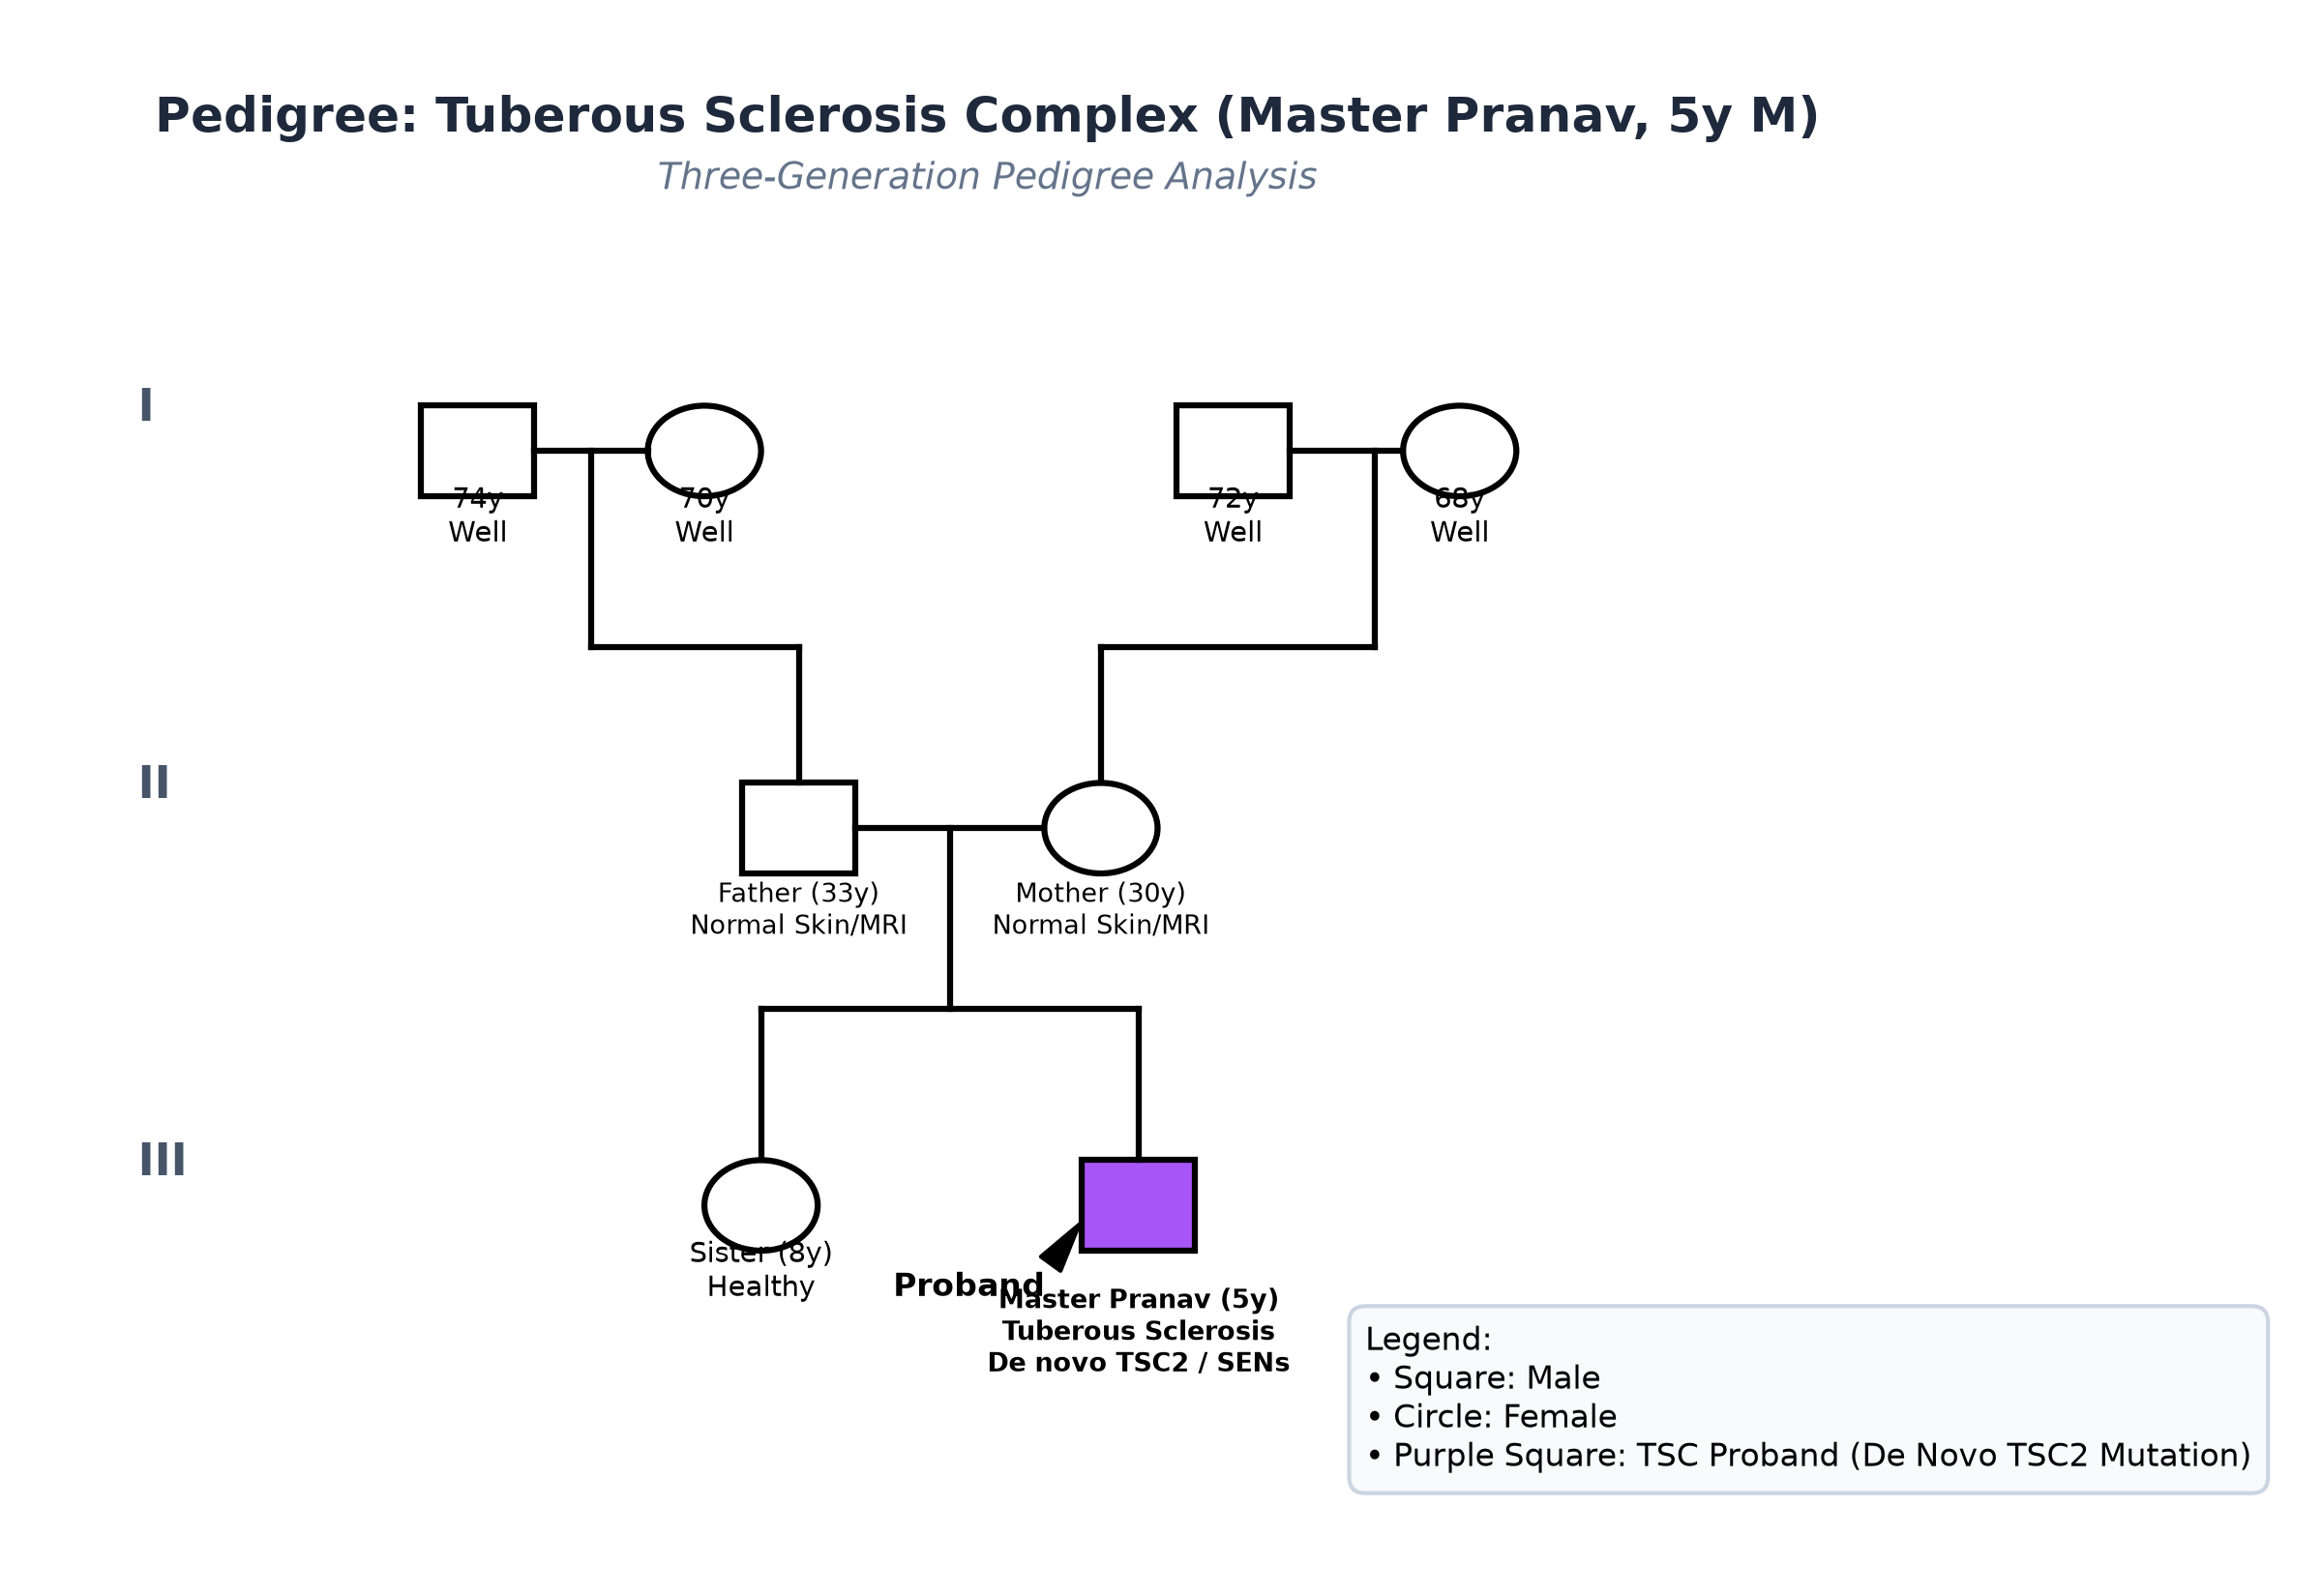
- Both parents (Father 33y, Mother 30y) underwent thorough clinical genetics evaluation: complete Wood's lamp skin examination was negative (zero ash-leaf macules), slit-lamp fundus was normal, and contrast-enhanced brain MRI was completely normal.
- Older sister (8 years old) is completely healthy with normal skin and intellect.
- Confirms a Spontaneous De Novo Pathogenic Mutation (responsible for $>70\%$ of all Tuberous Sclerosis cases).
Immunization History
- Fully immunized up to age according to the National Immunization Schedule.
Detailed Dietary History & 24-Hour Recall
The child consumes a typical South Indian vegetarian family diet:
| Food Item | Quantity | Calories (kcal) | Protein (g) |
|---|---|---|---|
| Cow's Milk | 400 mL | 260 | 13.0 |
| Idli with Ghee | 3 pieces | 220 | 5.5 |
| Boiled Rice | 1.5 cups | 240 | 4.8 |
| Sambar / Dal | 1.5 katoris | 150 | 6.5 |
| Curd Rice | 1 bowl | 160 | 5.0 |
| Banana | 1 medium | 90 | 1.1 |
| Snacks / Biscuits | 2 pieces | 80 | 1.2 |
| Total Observed Daily Intake | — | 1200 kcal | 37.1 g |
24-Hour Recall Deficit Analysis (ICMR-NIN 2024 Standards)
$$ \text{Ideal Body Weight (IBW for 5 years, 50th centile WHO)} = 18.3\text{ kg} $$| Nutrient | Expected Intake (ICMR-NIN 2024 for IBW 18.3 kg) | Observed Intake | Deficit | Percentage Deficit |
|---|---|---|---|---|
| Energy (kcal) | $18.3\text{ kg} \times 70\text{ kcal/kg} = 1281\text{ kcal}$ | 1200 kcal | 81 kcal | 6.3% Deficit (Optimal) |
| Protein (g) | $18.3\text{ kg} \times 1.05\text{ g/kg} = 19.2\text{ g}$ | 37.1 g | Nil (Adequate) | 0% Deficit |
The expected calories and proteins should be calculated from the ideal body weight, not from current weight.
Socioeconomic & KAP
- Modified BG Prasad Socioeconomic Class II. Parents have good insight into the multisystem nature of TSC and understand the need for regular surveillance of the brain, kidneys, and eyes.
Summary of History
Master Pranav, a 5-year-old male child, presents with classical features of Tuberous Sclerosis: history of infantile spasms at 6 months treated with Vigabatrin, multiple hypomelanotic macules since infancy, facial angiofibromas in a malar distribution, lumbosacral shagreen patch, and mild cognitive delay with focal epilepsy, with parents screening negative.
Provisional Clinical Diagnosis: Neurocutaneous Syndrome, clinically diagnostic of Definitive Tuberous Sclerosis Complex (TSC), complicated by Controlled Epilepsy, Facial Angiofibromas, and Tuberous Sclerosis-Associated Neuropsychiatric Disorder (TAND).
General Physical & Dermatological Examination
- General Appearance: Alert, hyperactive young boy who wanders around the examination room, touches objects incessantly; afebrile; no pallor, icterus, cyanosis, or pedal edema.
- Vitals:
- Heart Rate: 90 beats/minute, regular.
- Respiratory Rate: 20 breaths/minute.
- Blood Pressure: $94/58\text{ mmHg}$ (Normal; important to screen for renal AML-related hypertension).
- Anthropometry:
- Weight: 18.0 kg (50th centile WHO).
- Height: 109.0 cm (50th centile WHO).
- Head Circumference: 51.0 cm (50th centile, normocephalic).
- BMI: $15.1\text{ kg/m}^2$ (Normal).
Detailed Dermatological & Wood's Lamp Examination
- Wood's Lamp Examination (UV Light $365\text{ nm}$ in Darkened Room):
- Hypomelanotic Macules (Ash-Leaf Spots): Total of 6 discrete, polygonal, lanceolate macules fluorescing bright chalky-white:
- 2 over the back ($3.5 \times 1.5\text{ cm}$ and $2.0 \times 1.0\text{ cm}$).
- 2 over the left thigh ($4.0 \times 1.8\text{ cm}$).
- 1 over the right lower abdomen ($2.5 \times 1.0\text{ cm}$).
- 1 over the right forearm ($1.5 \times 0.8\text{ cm}$).
- All lesions are $>5\text{ mm}$ with rounded lateral borders and tapering ends (Major Feature).
- Confetti Macules: Multiple tiny ($1-2\text{ mm}$) scattered punctate hypopigmented spots over both anterior tibial surfaces (Minor Feature).
- Hypomelanotic Macules (Ash-Leaf Spots): Total of 6 discrete, polygonal, lanceolate macules fluorescing bright chalky-white:
- Facial Examination:
- Facial Angiofibromas (Adenoma Sebaceum): Symmetrical cluster of reddish-brown, smooth, firm, telangiectatic hamartomatous papules ($1-3\text{ mm}$) distributed over the bridge of the nose, nasolabial folds, and malar eminences in a butterfly pattern, with complete sparing of the upper cutaneous lip (Major Feature).
- Forehead Plaque: A faint, yellowish-pink, flat fibrous plaque ($1.5 \times 1.0\text{ cm}$) over the right forehead.
- Lumbosacral Spine Examination:
- Shagreen Patch: A single, large ($4.5 \times 3.0\text{ cm}$), firm, elevated, yellowish-flesh-colored plaque with a bumpy, cobblestone texture resembling an orange peel (peau d'orange) located over the lower lumbar spine (Major Feature).
- Nail Bed & Oral Cavity Examination:
- Nails: Currently no periungual fibromas (Koenen tumors).
- Oral Cavity: High arched palate; anterior teeth demonstrate $>5$ discrete, pinpoint enamel pits on the labial surface of the upper incisors (Minor Feature); gingival fibroma absent.
- Ophthalmic Slit-Lamp & Indirect Ophthalmoscopy:
- Pupils equal and reactive.
- Fundus: A solitary, mulberry-like, elevated, calcified Retinal Astrocytic Hamartoma ($1.5\text{ mm}$) noted along the superior temporal vascular arcade of the right retina; no visual impairment (Major Feature).
Detailed Systemic Examination
Central Nervous System & Neuropsychiatric Evaluation
- Higher Functions & Behavior: Alert; hyperactive; difficulty sustaining attention; speech is fluent but repetitive; receptive language intact; Childhood Autism Rating Scale (CARS) score is 28 (mild sensory processing atypicality / TAND).
- Cranial Nerves: Normal; extraocular movements full; no facial asymmetry.
- Motor System: Bulk normal; muscle tone normal; power 5/5 in all four extremities; deep tendon reflexes $2+$ symmetrical; plantars flexor. Normal coordination and gait.
Cardiovascular, Respiratory & Abdominal Systems
- Cardiovascular: Precordium quiet; apex in 4th intercostal space at midclavicular line; normal S1, S2; no murmurs; normal femoral pulses.
- Respiratory: Clear breath sounds bilaterally; no wheezes or crackles.
- Abdomen: Soft, non-tender; liver and spleen not palpable; bilateral renal angles free, no palpable kidney enlargement (renal AMLs are non-palpable currently).
Summary
Master Pranav, a 5-year-old male child, presents with classical features of Tuberous Sclerosis: history of infantile spasms successfully treated with Vigabatrin, multiple ash-leaf macules (>3 under Wood's lamp), facial angiofibromas, lumbosacral shagreen patch, dental enamel pits, retinal astrocytic hamartoma, and mild TAND, with parents screening negative.
Final Clinical Diagnosis: Definitive Tuberous Sclerosis Complex (TSC), secondary to a De Novo Heterozygous Pathogenic Mutation in the TSC2 Gene (Tuberin), presenting with 8 Major Diagnostic Features, complicated by Controlled Epilepsy, Facial Angiofibromas, and Tuberous Sclerosis-Associated Neuropsychiatric Disorder (TAND).
Differential Diagnosis of Neurocutaneous Disorders
| Disorder | Points IN FAVOR | Points AGAINST |
|---|---|---|
| Tuberous Sclerosis Complex (TSC) | Ash-leaf spots, facial angiofibromas, shagreen patch, infantile spasms, SENs, retinal hamartoma | Primary Diagnosis (8 Major Features) |
| Neurofibromatosis Type 1 (NF-1) | Neurocutaneous syndrome, learning difficulties | Skin shows Café-au-lait macules (brown spots, not white), axillary freckles (Crowe sign), neurofibromas, and Lisch nodules; ash-leaf spots are ABSENT |
| Sturge-Weber Syndrome | Epilepsy in infancy, facial cutaneous lesion | Facial lesion is a unilateral vascular Port-Wine Stain strictly in the V1/V2 trigeminal distribution; intracranial tram-track gyral calcification |
| Hypomelanosis of Ito | Hypopigmented skin lesions, seizures | Hypopigmentation follows Blaschko's lines in whorled, streaky, marble-cake patterns; no angiofibromas, SENs, or shagreen patch |
| Incontinentia Pigmenti | Seizures, skin lesions in childhood | X-linked dominant in females; skin lesions progress through 4 stages: blisters $\to$ verrucous papules $\to$ hyperpigmented streaks $\to$ atrophic pale lines |
Investigation Protocol & Multi-Organ Staging
flowchart TD
    A["Child with Hypomelanotic Macules, Facial Angiofibromas & Seizure History"] --> B["Wood's Lamp Skin Exam: Identify Lanceolate Ash-Leaf & Confetti Macules"]
    B --> C["Brain MRI with Contrast: Identify Cortical Tubers, SENs & Monitor for SEGA"]
    C --> D["Echocardiography: Screen for Cardiac Rhabdomyomas (Ventricular Septum)"]
    D --> E["Abdominal MRI / Ultrasound: Screen for Bilateral Renal Angiomyolipomas (AMLs)"]
    E --> F["Dilated Indirect Ophthalmoscopy: Retinal Astrocytic Hamartomas"]
    F --> G["Molecular Genetics: Next-Generation Sequencing of TSC1 and TSC2 Genes"]
    G --> H["Multidisciplinary Management: Anticonvulsants + Topical Sirolimus + Everolimus Protocol"]
1. 2021 International TSC Diagnostic Consensus Score Sheet
| Diagnostic Feature | Category | Present in Master Pranav? | Diagnostic Status |
|---|---|---|---|
| $\ge 3$ Hypomelanotic Macules | Major Feature | Yes (6 Macules under Wood's lamp) | Major Feature #1 |
| Angiofibromas ($\ge 3$) / Fibrous Plaque | Major Feature | Yes (Facial Angiofibromas + Plaque) | Major Feature #2 |
| Shagreen Patch | Major Feature | Yes (Lumbosacral $4.5 \times 3\text{ cm}$) | Major Feature #3 |
| Multiple Cortical Tubers | Major Feature | Yes (8 Tubers on Brain MRI) | Major Feature #4 |
| Multiple Subependymal Nodules (SENs) | Major Feature | Yes (Multiple on MRI) | Major Feature #5 |
| Subependymal Giant Cell Astrocytoma | Major Feature | Yes ($1.2\text{ cm}$ at Foramen of Monro) | Major Feature #6 |
| Retinal Astrocytic Hamartoma | Major Feature | Yes (Right Retina) | Major Feature #7 |
| Cardiac Rhabdomyoma | Major Feature | Yes ($6\text{ mm}$ apical remnant on Echo) | Major Feature #8 |
| Dental Enamel Pits ($>3$) | Minor Feature | Yes ($>5$ pits on upper incisors) | Minor Feature #1 |
| Confetti Skin Lesions | Minor Feature | Yes (Bilateral shins) | Minor Feature #2 |
| Diagnostic Conclusion | — | 8 Major + 2 Minor Features | Definitive TSC Confirmed |
2. Neuroimaging & Multi-Organ Surveillance
- Brain MRI with Contrast (T1, T2, FLAIR):
- Cortical Tubers: Multiple (8) wedge-shaped areas of high T2/FLAIR signal in the subcortical white matter and cortex with expanded overlying gyri.
- Subependymal Nodules (SENs): Multiple small ($2-5\text{ mm}$) nodules projecting into the lateral ventricles along the caudate margin, showing T1 hyperintensity and calcification.
- Subependymal Giant Cell Astrocytoma (SEGA): A well-circumscribed, enhancing mass measuring $12 \times 10\text{ mm}$ located at the left Foramen of Monro; currently no ventriculomegaly or hydrocephalus (Evan's index $0.26$, normal); baseline established for serial monitoring.
- Transthoracic Echocardiography:
- Solitary, small, well-demarcated echogenic mass ($6 \times 5\text{ mm}$) in the left ventricular apical myocardium (Regressing Cardiac Rhabdomyoma); no left ventricular outflow tract obstruction; normal ejection fraction ($66\%$).
- Renal Ultrasound & Contrast MRI:
- Bilateral small, echogenic cortical lesions: two in right kidney ($1.2\text{ cm}$ and $0.8\text{ cm}$) and one in left kidney ($1.0\text{ cm}$), characteristic of Renal Angiomyolipomas (AMLs); all $<3\text{ cm}$ (low risk for acute hemorrhage); normal renal function (Creatinine $0.4\text{ mg/dL}$, Blood Pressure normal).
- Molecular Genetics: NGS panel identified a heterozygous nonsense pathogenic mutation c.5227C>T (p.Arg1743Ter) in Exon 41 of the TSC2 Gene on chromosome 16p13.3. Parental testing confirmed neither parent carries the mutation (De Novo mutation).
Comprehensive Multidisciplinary Management Plan
1. Neurological & Targeted mTOR Inhibitor Strategy
- Seizure Management: Continue oral Levetiracetam at $30\text{ mg/kg/day}$ divided twice daily; child has been seizure-free for 14 months.
- Protocolized SEGA Surveillance & Everolimus Criteria:
- Schedule serial brain MRI every 6 to 12 months.
- Indications for Oral Everolimus (Afinitor): If the SEGA grows by $>2-3\text{ mm}$, causes ventricular enlargement, or produces symptoms of raised ICP:
- Initiate Everolimus at $4.5\text{ mg/m}^2/\text{day}$ orally, targeting therapeutic blood trough levels of $5-15\text{ ng/mL}$.
- Rationale: Directly inhibits hyperactive mTORC1, producing $>50\%$ volume shrinkage of SEGA, controlling refractory seizures, and shrinking renal AMLs simultaneously!
2. Dermatological & Renal Management
- Topical Sirolimus (Rapamycin) $0.1\%$ Gel:
- Applied once daily at bedtime to facial angiofibromas.
- Results: Reverses hamartomatous vascular papules within 3-6 months with minimal systemic absorption, avoiding painful laser ablation.
- Renal Angiomyolipoma Surveillance:
- Annual renal ultrasound and blood pressure monitoring.
- Counsel parents: If sudden severe flank pain or hematuria occurs, suspect acute AML rupture/hemorrhage (Wunderlich syndrome). Embolization or Everolimus indicated if AMLs grow $>3\text{ cm}$.
3. Neuropsychiatric & Developmental Care (TAND)
- Formal psychoeducational assessment for ADHD and learning support.
- Behavioral therapy and sensory integration therapy to improve attention span and classroom participation.