
Master Vivaan, a 2-year-old male child, born of a non-consanguineous marriage from Bengaluru, Karnataka, presented to the pediatric emergency with high-grade continuous fever for 7 days ($102-104^\circ\text{F}$) unyielding to paracetamol and oral antibiotics, bilateral non-purulent red eyes for 5 days, fiery red cracked lips and strawberry tongue for 4 days, swelling and redness of both hands and feet for 3 days, a red blotchy rash over trunk and diaper area for 3 days, and a painful right neck swelling for 2 days.
- High continuous remittent fever persisting for $\ge 5$ days
- Bilateral non-exudative conjunctival redness with limbic sparing
- Fiery red, dry, cracked lips and prominent red strawberry tongue
- Tense, indurated swelling and erythema of palms and soles
- Polymorphous maculopapular rash, marked in the perineum
- Unilateral painful cervical lymphadenopathy ($\ge 1.5$ cm)
- Striking erythema, induration, or crusting at the BCG vaccination scar
HOPI
The history is dated back to 7 days ago when the child acutely developed high-grade fever reaching $103-104^\circ\text{F}$.
Kawasaki Disease is an acute, self-limited medium-vessel necrotizing vasculitis with a predilection for the coronary arteries. The window of opportunity to prevent fatal Coronary Artery Aneurysms (CAA) is within the first 10 days of fever onset by administering high-dose Intravenous Immunoglobulin (IVIG $2\text{ g/kg}$). Inquire systematically about the 5 principal clinical criteria. In Indian infants, always inspect and ask specifically about BCG site erythema (present in $>75\%$ of affected toddlers). Ask about irritability disproportionate to fever (aseptic meningitis).
- High Continuous Fever (7 Days Duration):
- Spiking up to $104^\circ\text{F}$ ($40.0^\circ\text{C}$), remittent, unyielding to oral amoxicillin-clavulanate prescribed by a local pediatrician.
- Child is intensely irritable, inconsolable, and refuses to be put down Points to sterile cerebral vasculitis / aseptic meningitis characteristic of acute Kawasaki disease.
- Bilateral Eye Redness:
- Appeared on Day 3 of fever. Bilateral, symmetrical injection of the white part of the eyes (bulbar conjunctiva).
- Completely devoid of purulent discharge, pus, eye mattering, or crusting; eyelids do not stick together in the morning Rules out bacterial or adenovirus conjunctivitis; perilimbal sparing is classic for Kawasaki vasculitis.
- Oral Cavity Changes:
- Lips became fiery red, dry, severely cracked, and bled on touch.
- Tongue developed prominent raised red spots resembling the surface of a strawberry (Strawberry tongue) with diffuse pharyngeal erythema.
- Extremity Changes & Inability to Walk:
- Developed tense, brawny, non-pitting edema and erythema of both palms and soles on Day 5.
- The child cried when his feet were touched and completely refused to stand or walk.
- Polymorphous Skin Rash:
- Maculopapular erythematous rash appeared on the trunk and groin.
- Mother noted intense fiery redness in the diaper area with early sheet-like peeling of skin (perineal desquamation).
- Cervical Swelling:
- Rapidly developing painful swelling on the right side of the neck for the past 48 hours.
- BCG Scar Reactivation:
- Mother observed that the old BCG vaccination scar on the left upper arm became swollen, raised, bright red, and crusted over the last 3 days Cross-reactive T-cell response between mycobacterial HSP65 and human endothelial HSP63.
- Negative History:
- No history of watery purulent rhinorrhea, harsh barking cough, or stridor Rules out measles or viral respiratory infections.
- No history of vesicular fluid-filled lesions or honey-colored crusts Rules out varicella or staphylococcal scalded skin syndrome.
- No history of sudden flaccid paralysis, seizures, or vomiting.
Past History
- Born full-term, birth weight 3.2 kg; uneventful neonatal course.
- No history of recurrent wheezing, atopy, or drug allergies.
Family history
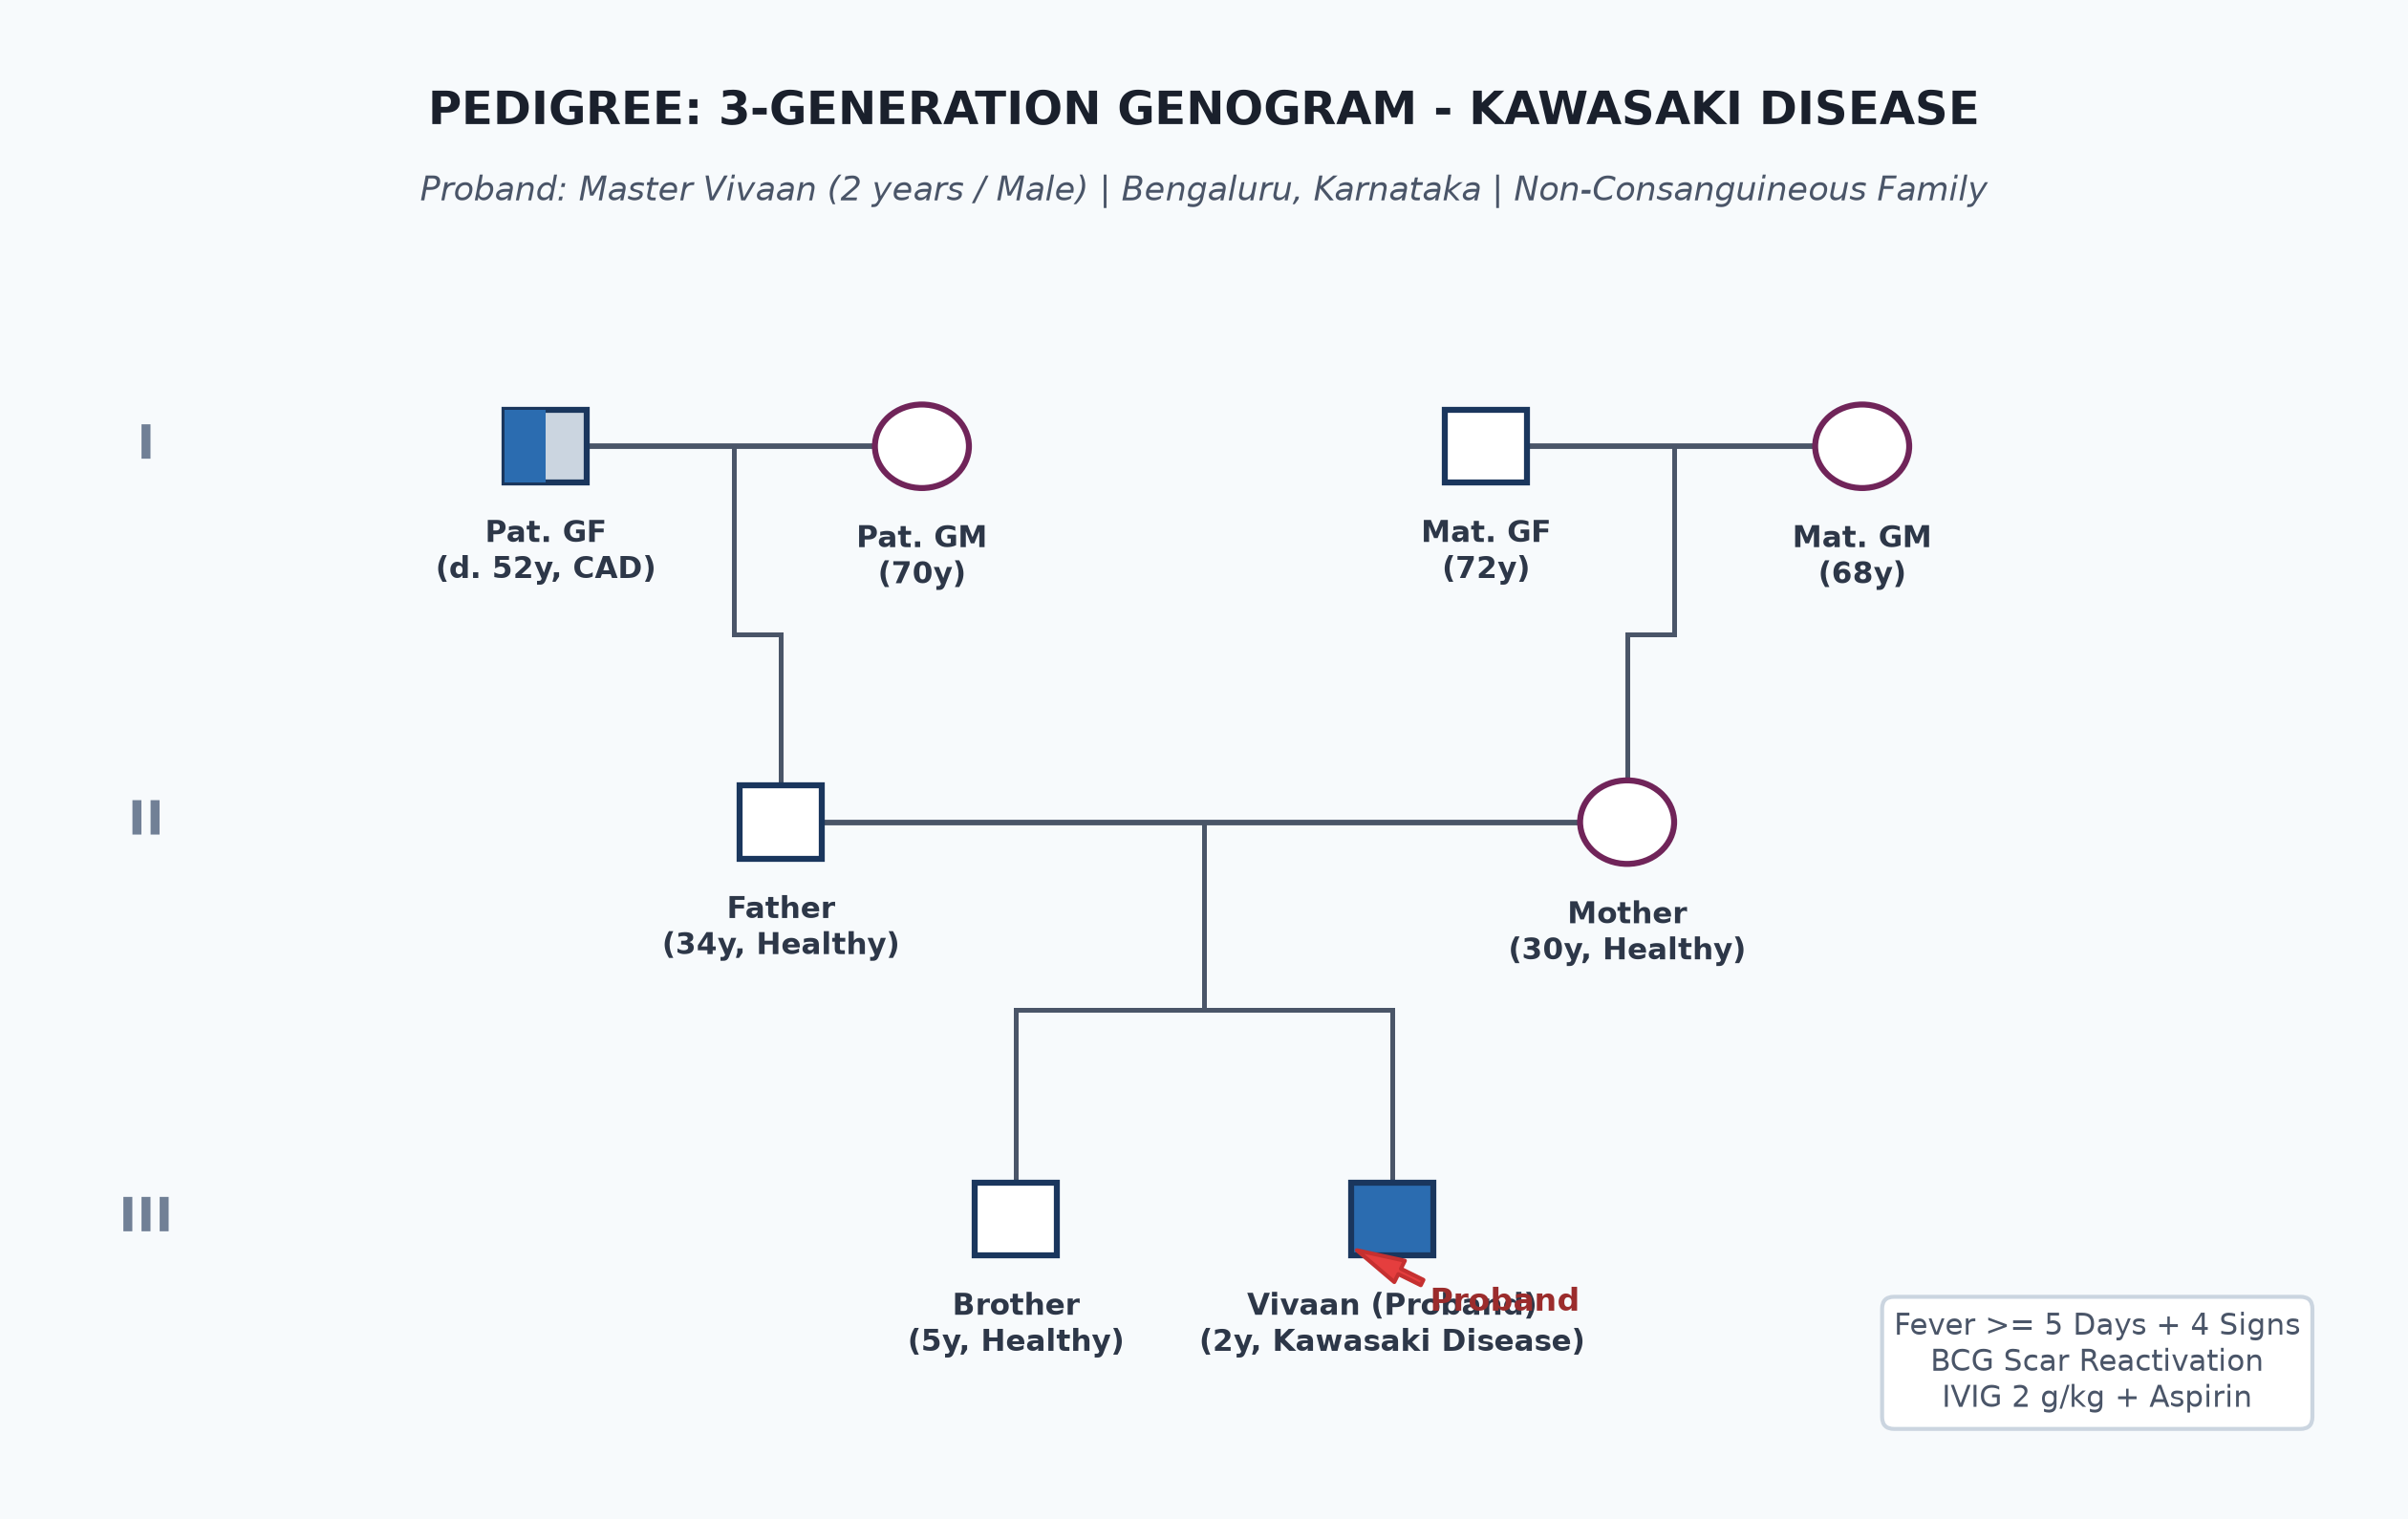
- Non-consanguineous marriage.
- Father 34 years, software engineer; Mother 30 years, homemaker; both healthy.
- Elder brother (5 years old) is completely healthy.
- Paternal Grandfather: Had premature myocardial infarction at 52 years of age.
Immunization history
- Received BCG and OPV-0 at birth (healed scar present on left deltoid).
- Fully immunized up to age including Pentavalent, OPV, fIPV, Rotavirus, PCV, and MR-1 at 9 months.
Dietary history
- Consumes a mixed family diet; currently refusing solid foods due to lip fissures and strawberry tongue.
24-Hour Recall Deficit Analysis
$$ \text{Ideal Body Weight (IBW for 2 years, 50th centile WHO)} = 12.2\text{ kg} $$| Nutrient | Expected Intake (ICMR-NIN 2024 for IBW 12.2 kg) | Observed Intake | Deficit | Percentage Deficit |
|---|---|---|---|---|
| Energy (kcal) | $12.2\text{ kg} \times 83\text{ kcal/kg} = 1012\text{ kcal}$ | 520 kcal | 492 kcal | 48.6% Deficit |
| Protein (g) | $12.2\text{ kg} \times 1.07\text{ g/kg} = 13.0\text{ g}$ | 6.8 g | 6.2 g | 47.7% Deficit |
Socioeconomic and KAP
- Modified BG Prasad Socioeconomic Class I (Upper Class).
- Parents aware of the urgency of cardiac evaluation due to high fever and eye redness.
Summary of History
Master Vivaan, a 2-year-old male child born of non-consanguineous parentage, presented on Day 7 of illness with high continuous fever ($104^\circ\text{F}$), bilateral non-exudative conjunctivitis, strawberry tongue, indurated erythema of palms and soles, perineal desquamating exanthem, right cervical lymphadenopathy, and BCG scar reactivation, with extreme irritability.
I would like to consider a diagnosis of Complete (Classic) Kawasaki Disease on Day 7 of illness, requiring immediate echocardiographic coronary evaluation and high-dose IVIG therapy.
General head to toe examination
- Behavioral State: Prechtl State 4/5 (Extremely irritable, restless, crying inconsolably, clings to mother).
- Vitals:
- Heart Rate: 144 beats/minute, regular, bounding volume (tachycardia disproportionate to fever, suggesting myocarditis).
- Respiratory Rate: 28 breaths/minute, regular.
- Blood Pressure: $88/54\text{ mmHg}$ ($50^{\text{th}}$ centile, normotensive).
- Temperature: $39.6^\circ\text{C}$ ($103.3^\circ\text{F}$).
- Capillary Refill Time: $<2$ seconds; extremities warm.
- Anthropometry:
| Parameter | Observed | Expected (50th WHO) | Centile | Inference |
|---|---|---|---|---|
| Weight | 11.8 kg | 12.2 kg | $50^{\text{th}}\text{ centile}$ | Normal baseline nutrition |
| Length | 86.5 cm | 87.0 cm | $50^{\text{th}}\text{ centile}$ | Normal Stature |
| Head Circumference | 48.2 cm | 48.5 cm | Normal | Age-appropriate |
- Comprehensive Evaluation of AHA Principal Criteria:
- Bilateral Bulbar Conjunctival Injection: Present bilaterally, glassy red, non-exudative; distinct clear halo around the limbus (perilimbal sparing); no photophobia or discharge.
- Oral Cavity Changes: Lips swollen, deep red, with vertical bleeding fissures; Strawberry Tongue with hypertrophied fungiform papillae protruding through a red mucosal surface; diffuse pharyngeal hyperemia; no tonsillar exudate.
- Extremity Changes: Tense, brawny, painful non-pitting edema of bilateral palms and soles with fiery erythema; refusal to bear weight.
- Polymorphous Exanthem: Diffuse, non-vesicular maculopapular rash over the trunk; prominent confluent erythema in the perineal region with fine superficial desquamation.
- Cervical Lymphadenopathy: Solitary, firm, moderately tender right anterior cervical lymph node measuring $2.0 \times 1.5\text{ cm}$; non-fluctuant, overlying skin faintly erythematous.
- BCG Scar Reactivation: The $6\text{ mm}$ BCG scar over the left deltoid is distinctly raised, indurated, fiery red, and crowned by a superficial crust.
Systemic Examination
Cardiovascular System (CVS)
- Precordium hyperactive; apex beat in 4th left intercostal space, $0.5\text{ cm}$ lateral to midclavicular line.
- Tachycardia (144 bpm) with Gallop Rhythm ($S_3$ audible at apex) Points to acute Kawasaki myocarditis.
- Grade 2/6 soft systolic murmur heard at apex (transient mitral regurgitation due to papillary muscle inflammation); JVP not raised.
Abdomen
- Symmetrically full, soft; mild right upper quadrant tenderness on deep palpation; liver palpable 2.0 cm below right costal margin, soft; spleen not palpable. (Gallbladder hydrops is a recognized finding).
Respiratory & Central Nervous System
- Clear breath sounds bilaterally. Neurological: Irritable, no neck stiffness, anterior fontanelle closed, cranial nerves intact.
Summary
Master Vivaan, a 2-year-old male child, presents on Day 7 of high continuous fever with all 5 principal AHA criteria: bilateral non-exudative perilimbal-sparing conjunctivitis, cracked lips with strawberry tongue, brawny edema of palms and soles, polymorphous perineal-accentuated exanthem, and unilateral cervical lymphadenopathy ($2.0\text{ cm}$), accompanied by BCG scar reactivation and sinus tachycardia with gallop rhythm (myocarditis).
Final Clinical Diagnosis: Complete (Classic) Kawasaki Disease on Day 7 of illness, complicated by acute myocarditis, requiring emergent high-dose IVIG ($2\text{ g/kg}$) and oral Aspirin therapy to prevent coronary artery aneurysm formation.
Differential Diagnosis
| Condition | Points IN FAVOR | Points AGAINST |
|---|---|---|
| Kawasaki Disease (Complete) | Fever $\ge 5$ days, 5/5 AHA criteria, BCG scar erythema, extreme irritability, myocarditis gallop | Primary Clinical Diagnosis |
| Measles (Rubeola) | High fever, conjunctivitis, maculopapular rash, lymphadenopathy | Measles features the "3 Cs" (Cough, Coryza, Conjunctivitis with purulent photophobia), Koplik spots on buccal mucosa, and rash begins behind ears spreading downwards (not perineal) |
| Systemic JIA (sJIA) | High fever, rash, lymphadenopathy, high inflammatory markers | Fever in sJIA is quotidian (spikes once daily and normalizes); rash is evanescent salmon-pink; sJIA lacks strawberry tongue and BCG reactivation |
| Scarlet Fever (Group A Strep) | Strawberry tongue, fever, red rash | Scarlet fever rash has sandpaper texture, Pastia lines in flexures, circumoral pallor, and purulent tonsillar exudate; responds dramatically to penicillin |
| Multisystem Inflammatory Syndrome in Children (MIS-C) | Kawasaki-like phenotype, strawberry tongue, conjunctivitis | MIS-C occurs in older children ($8-12$y), presents with severe vasodilatory shock/hypotension, marked ventricular dysfunction, and positive COVID-19 history |
| Stevens-Johnson Syndrome (SJS) | Mucosal crusting, conjunctivitis, rash | SJS is precipitated by drugs (NSAIDs, antiepileptics), features targetoid bullous lesions with skin detachment (Nikolsky positive), and severe hemorrhagic mucosal necrosis |
Investigation Protocol & Diagnostic Workup
flowchart TD
    A["Child with Fever ≥ 5 Days & ≥ 4 Principal Criteria"] --> B["Stat Transthoracic Echocardiography & ECG"]
    B --> C["Establish Baseline Coronary Diameters & Calculate Z-Scores"]
    C --> D["Stat CBC, ESR, CRP, Platelets, LFT, RFT, Sterile Pyuria Check"]
    D --> E["Immediately Administer IVIG 2 g/kg (Over 10-12 Hours)"]
    E --> F["Co-Administer Oral Aspirin (30-50 mg/kg/day divided Q6H)"]
    F --> G{"Fever Persistent ≥ 36 Hours Post-IVIG?"}
    G -->|Yes: IVIG Resistance| H["Administer 2nd IVIG (2 g/kg) OR Pulse Methylprednisolone OR Infliximab"]
    G -->|No: Defervescence Achieved| I["Switch to Low-Dose Antiplatelet Aspirin (3-5 mg/kg/day) for 6-8 Weeks"]
1. Cardiovascular Evaluation (The Critical Test)
- Transthoracic Echocardiography (Day 7 of Illness):
- Left Main Coronary Artery (LMCA): Internal lumen diameter $3.6\text{ mm}$ ($Z\text{-score} = +3.2$ $\rightarrow$ Small Coronary Artery Aneurysm; normal $<2.0$).
- Left Anterior Descending (LAD): Diameter $2.8\text{ mm}$ ($Z\text{-score} = +2.6$ $\rightarrow$ Ectasia/Small Aneurysm).
- Right Coronary Artery (RCA): Diameter $2.5\text{ mm}$ ($Z\text{-score} = +2.1$).
- Left Ventricular Ejection Fraction (LVEF): $54\%$ (Mild myocardial systolic dysfunction / myocarditis).
- Trace pericardial effusion ($2\text{ mm}$ posterior echo-free space).
- 12-Lead ECG: Sinus tachycardia (144 bpm), prolonged PR interval ($0.16\text{ sec}$ $\rightarrow$ 1st degree AV block), flattened T waves in lateral leads (myocardial ischemia/inflammation).
2. Laboratory Markers of Vasculitis
- Complete Blood Count:
- Hemoglobin: $9.8\text{ g/dL}$ (Normocytic normochromic anemia).
- White Blood Cell Count: $19,800/\mu\text{L}$ ($78\%$ neutrophils with band forms).
- Platelet Count: $480,000/\mu\text{L}$ on Day 7 (expected to climb to $>800,000/\mu\text{L}$ in Weeks 2 to 3).
- Inflammatory Markers:
- ESR: $94\text{ mm/hr}$.
- CRP: $118\text{ mg/L}$ (Markedly elevated).
- Serum Biochemistry:
- Serum Albumin: $2.8\text{ g/dL}$ (Hypoalbuminemia reflecting severe capillary leak).
- Serum Sodium: $132\text{ mEq/L}$ (Hyponatremia $\le 133\text{ mEq/L}$ adds 2 points on Kobayashi score).
- Liver Enzymes: AST $86\text{ U/L}$, ALT $112\text{ U/L}$ (Transaminitis).
- Urine Routine (Uncentrifuged):
- Sterile Pyuria: $18-20\text{ WBCs/HPF}$ without bacteria (originates from urethral vasculitis).
Therapeutic Management Protocol (AHA 2017 Guidelines)
1. Primary Immunomodulatory Therapy (Initiated on Day 7)
- Intravenous Immunoglobulin (IVIG):
- Dose: $2.0\text{ g/kg}$ administered as a single continuous intravenous infusion over 10 to 12 hours.
- For this child ($11.8\text{ kg}$): Total dose $= \mathbf{23.6\text{ grams}}$ of IVIG.
- Mechanism: Rapidly suppresses systemic endothelial inflammation, neutralizes superantigens, downregulates cytokine production, and slashes the risk of coronary artery aneurysms from $25\%$ down to $<3-5\%$.
- Oral Aspirin (Acetylsalicylic Acid):
- Anti-Inflammatory Phase: $30\text{ to } 50\text{ mg/kg/day}$ divided into 4 doses (Q6H) orally ($100\text{ mg}$ Q6H) until the child has been afebrile for 48 to 72 hours.
- Antiplatelet Phase: Once afebrile, switch to low-dose Aspirin at $3\text{ to } 5\text{ mg/kg/day}$ as a single morning dose ($40-50\text{ mg}$ OD).
- Continue antiplatelet aspirin for 6 to 8 weeks post-onset, or indefinitely if coronary artery aneurysms persist on serial echocardiograms.
2. Monitoring & Follow-Up Protocol
- Repeat echocardiography at 2 weeks and 6 to 8 weeks post-illness onset to monitor for aneurysm progression, regression, or thrombosis.
- Defer all live virus vaccines (Measles, MMR, Varicella) for 11 months following high-dose IVIG.
- Influenza vaccination (inactivated) is mandatory while on long-term aspirin therapy to prevent Reye syndrome.