
Master Rohan, a 4-year-old male child, 2nd order offspring born of a non-consanguineous marriage from Bhopal, Madhya Pradesh, presented with complaints of progressive pallor and generalized lethargy for 4 weeks, high-grade intermittent fever for 3 weeks, severe deep-seated bone pain in both lower limbs with refusal to walk for 2 weeks, multiple spontaneous purpuric spots and nosebleeds for 10 days, and painless bilateral neck and groin swellings with abdominal distension for 1 week.
- Rapidly progressive pallor, fatigue, and exertional breathlessness (Erythroid suppression / severe anemia)
- Unexplained persistent or recurrent high fever and infections (Granulocytic suppression / neutropenia)
- Spontaneous petechiae, purpura, ecchymoses, and mucosal bleeds (Megakaryocytic suppression / thrombocytopenia)
- Deep-seated metaphysical bone pain, limp, or refusal to bear weight (Subperiosteal leukemic blast expansion)
- Painless lymphadenopathy and progressive abdominal distension (Hepatosplenomegaly)
- Testicular swelling in males or persistent early-morning headache and vomiting (Extramedullary sanctuaries)
HOPI
The history is dated back to 4 weeks ago when the mother first noticed that the child, previously very active, became progressively pale, listless, fatigued, and breathless after running short distances.
The triad of Pallor + Fever + Bleeding signifies bone marrow failure (pancytopenia). In ALL, leukemic blasts clonally expand in the marrow space, crowding out normal erythroid, myeloid, and megakaryocytic lineages. A critical diagnostic pitfall in pediatric examinations is the initial presentation with musculoskeletal symptoms: up to 25% of children with ALL present with severe, unprovoked metaphysical bone pain or limp, which is frequently misdiagnosed as septic arthritis or juvenile idiopathic arthritis. Inquire specifically whether systemic corticosteroids were administered prior to bone marrow examination (which lyses lymphoblasts and obscures flow cytometric classification!).
- Progressive Pallor and Fatigue:
- Insidious onset, noted 4 weeks ago; skin, palms, and conjunctiva turned progressively chalky-white.
- Child prefers being carried, tires easily on climbing stairs, and naps repeatedly during daytime.
- Intermittent High-Grade Fever:
- Started 3 weeks ago, spiking up to $103^\circ\text{F}$ ($39.4^\circ\text{C}$), occurring twice daily, associated with chills and profuse sweating.
- Partially responds to paracetamol; no associated cough, ear discharge, burning micturition, loose stools, or altered sensorium.
- Represents both neutropenic bacterial susceptibility and pyrogenic cytokine release (TNF-$\alpha$, IL-1) by leukemic blasts.
- Severe Bone Pain & Refusal to Walk:
- Developed 2 weeks ago; child complained of severe, deep aching pain in both lower thighs and shins, predominantly waking him from sleep at night.
- Gradually stopped walking and standing; cries and pulls legs up when parents attempt to make him bear weight.
- No history of trauma; pain is diffuse and metaphysical rather than localized to a single hot, erythematous joint Points to leukemic infiltration of bone marrow cavity with elevated intraosseous pressure.
- Bleeding Diathesis (Petechiae & Epistaxis):
- Appeared 10 days ago; mother noticed tiny, pinpoint, red non-blanching spots (petechiae) over the shins, forearms, and chest.
- Two episodes of spontaneous, painless epistaxis from the right nostril, self-controlled after 10 minutes of pinch pressure.
- Bleeding gums while brushing teeth; no hematemesis, melena, or gross hematuria.
- Lymphadenopathy & Abdominal Fullness:
- Noticed bilateral painless, non-tender swellings in the sides of the neck and groin 1 week ago.
- Abdomen appears progressively full; child feels early satiety after drinking small amounts of milk.
- Negative Inquiries:
- No history of prior steroid intake.
- No morning headache, projectile vomiting, seizures, or diplopia (rules out overt CNS leukemia).
- No scrotal enlargement noted by mother.
Past history
- No previous hospital admissions, blood transfusions, or prolonged febrile illnesses.
- No history of easy bruising or bleeding tendencies in infancy.
Antenatal, natal and postnatal history
- Mother was a 28-year-old registered multigravida; uneventful antenatal period, no exposure to ionizing radiation, maternal infections, or chemotherapeutic drugs.
- Full-term normal vaginal delivery at a tertiary hospital; birth weight 3.1 kg; cried immediately at birth.
- Neonatal period was uneventful; no prolonged jaundice or neonatal intensive care admission.
Development history
- Gross Motor: Walked independently by 13 months. (Currently bedbound due to leukemic bone pain).
- Fine Motor: Scribbled at 15 months, tower of 6 cubes at 22 months.
- Language: Two-word phrases by 24 months, speaks full sentences fluently.
- Social: Interactive, feeds with spoon, plays with peers.
- Developmental Quotient (DQ): Normal (~100%) across all developmental domains.
Family history
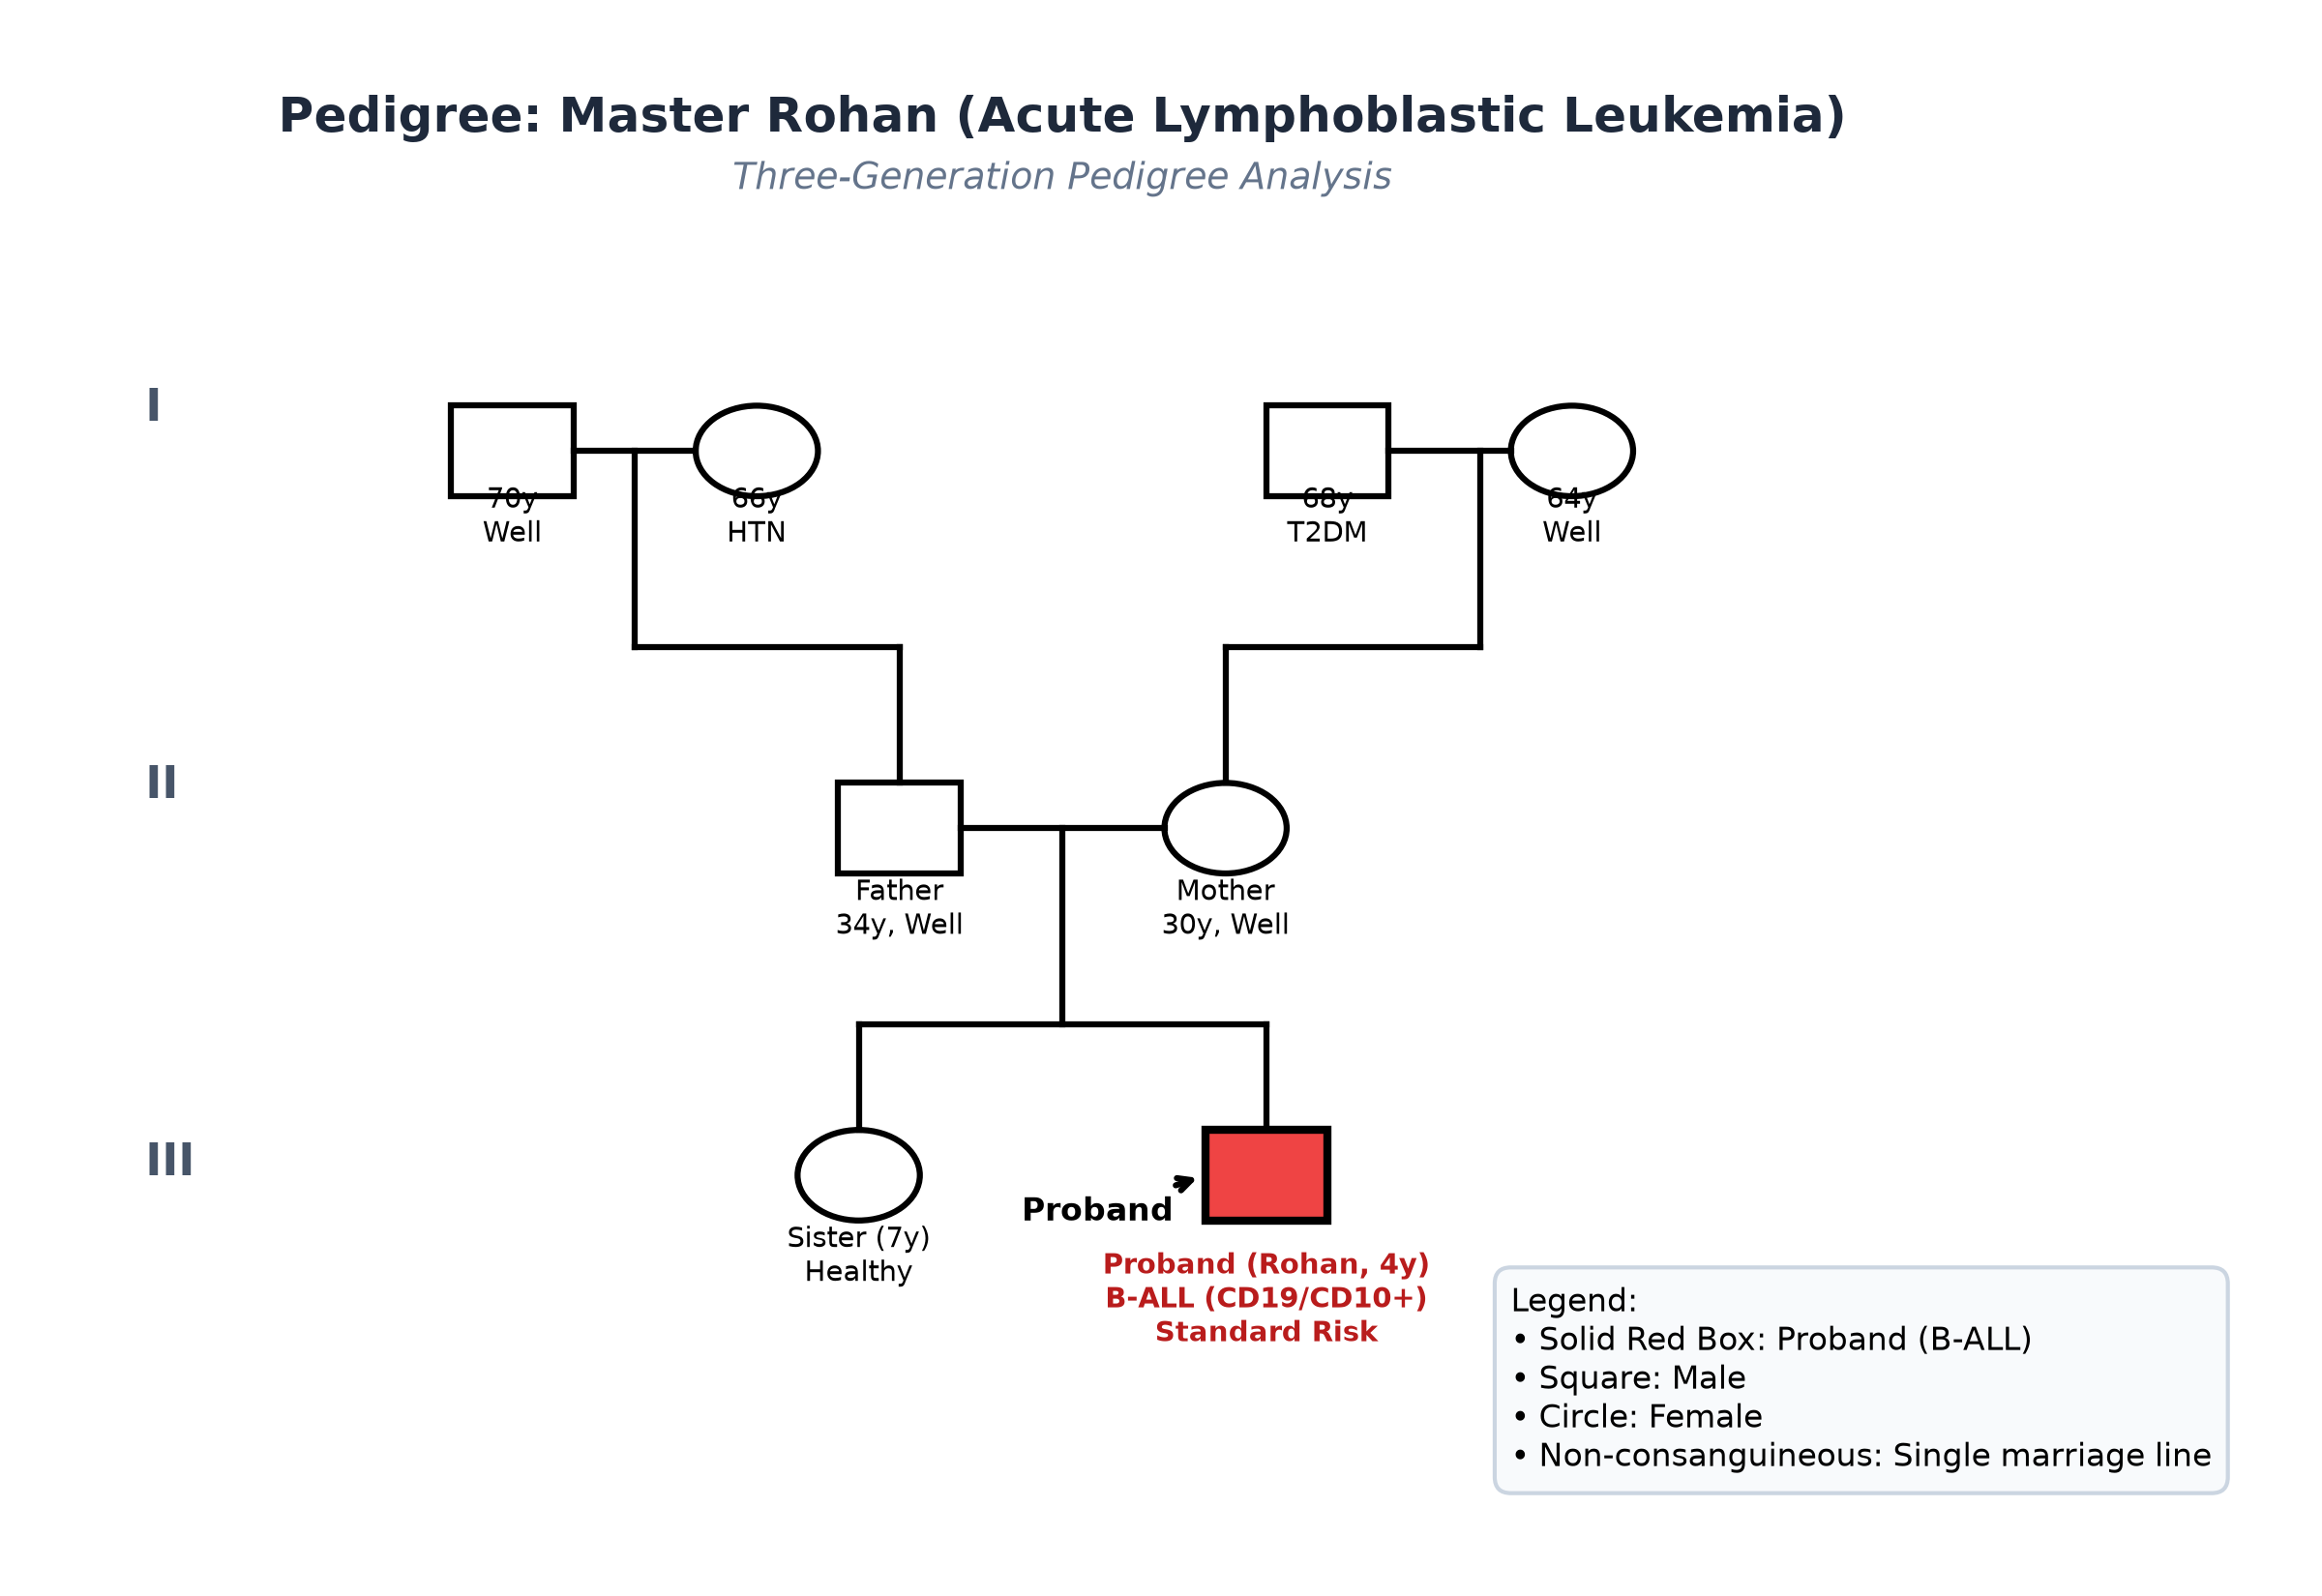
- Born of non-consanguineous Hindu parentage.
- Father 34 years, clerk, healthy; Mother 30 years, homemaker, healthy.
- Elder sister (7 years old) is attending school, completely healthy.
- No family history of childhood leukemia, lymphoma, brain tumors, or soft-tissue sarcomas (Li-Fraumeni syndrome).
Immunization history
- Fully immunized for age as per the National Immunization Schedule (BCG, OPV, Pentavalent, Rotavirus, PCV, MR).
Dietary history
- Prior to illness, consumed a balanced semi-solid and solid diet. Over the past 4 weeks, intake decreased by >45% due to fatigue and anorexia.
| Food Item | Quantity | Calories (kcal) | Protein (g) |
|---|---|---|---|
| Cow's Milk (toned) | 250 mL | 150 | 8.0 |
| Roti (whole wheat, 1) | 30 g flour | 102 | 3.5 |
| Boiled Rice | 80 g cooked | 104 | 2.1 |
| Moong Dal (thin, 1 small katori) | 20 g raw | 68 | 4.4 |
| Mashed Khichdi | 1 small katori | 130 | 3.2 |
| Biscuits | 2 pieces | 70 | 1.1 |
| Banana | 1 small (50 g) | 46 | 0.6 |
| Total Observed Daily Intake | — | 670 kcal | 22.9 g |
24-Hour Recall Deficit Analysis
$$ \text{Ideal Body Weight (IBW for 4 years, 50th centile WHO)} = 16.3\text{ kg} $$| Nutrient | Expected Intake (ICMR-NIN 2024 for IBW 16.3 kg) | Observed Intake | Deficit | Percentage Deficit |
|---|---|---|---|---|
| Energy (kcal) | $16.3\text{ kg} \times 74\text{ kcal/kg} = 1206\text{ kcal}$ | 670 kcal | 536 kcal | 44.4% Deficit |
| Protein (g) | $16.3\text{ kg} \times 1.0\text{ g/kg} = 16.3\text{ g}$ | 22.9 g | Nil (Adequate) | 0% Deficit |
The expected calories and proteins should be calculated from the ideal body weight, not from current weight.
Socioeconomic and KAP
- Modified BG Prasad Socioeconomic Class III (Middle Class).
- Lives in a pucca house with piped drinking water and indoor sanitation.
- Parents deeply distressed by sudden onset of illness and spontaneous bleeding.
Summary of History
Master Rohan, a 4-year-old male child, presents with a 4-week history of rapidly progressive pallor, fatigue, high-grade intermittent fever, refusal to bear weight due to nocturnal metaphysical bone pain, petechiae, epistaxis, and bilateral cervical lymphadenopathy with abdominal fullness, without prior steroid exposure or overt neuro-deficits.
I would like to consider a provisional clinical diagnosis of Acute Leukemia (likely B-Cell Acute Lymphoblastic Leukemia - ALL) presenting with tri-lineage bone marrow failure and extramedullary reticuloendothelial infiltration, categorized under NCI Standard Risk.
General head to toe examination
- Behavioral State: Conscious, irritable, pale, prefers lying still in supine position with flexed knees.
- Vitals:
- Heart Rate: 134 beats/minute, regular, bounding volume (hyperdynamic circulation secondary to severe anemia).
- Respiratory Rate: 26 breaths/minute, regular, no retractions.
- Blood Pressure: $94/56\text{ mmHg}$ ($50^{\text{th}}$ centile, normotensive).
- Temperature: $38.8^\circ\text{C}$ ($101.8^\circ\text{F}$) axillary.
- Capillary Refill Time: $<2$ seconds.
- Anthropometry:
| Parameter | Observed | Expected (50th WHO) | Z-score / Centile | Inference |
|---|---|---|---|---|
| Weight | 15.0 kg | 16.3 kg | $-0.5\text{ to } -1.0\text{ SD}$ | Acute weight loss of 1.3 kg (~8%) |
| Pre-morbid Weight | 16.3 kg | 16.3 kg | $50^{\text{th}}\text{ centile}$ | Normal baseline nutritional status |
| Height | 103.0 cm | 103.0 cm | $50^{\text{th}}\text{ centile}$ | Normal Stature (No stunting) |
| Weight-for-Height | 15.0 kg for 103 cm | 16.3 kg | $-1.0\text{ SD}$ | Mild acute wasting |
| Head Circumference | 49.8 cm | 50.0 cm | Normal | Age-appropriate |
| BMI | $14.1\text{ kg/m}^2$ | $15.3\text{ kg/m}^2$ | $-0.8\text{ SD}$ | Normal BMI |
- General Physical Findings:
- Pallor: Severe chalky pallor visible on palpebral conjunctiva, buccal mucosa, nail beds, and palmar creases.
- Petechiae & Purpura: Multiple non-blanching pinpoint petechiae (1 to 2 mm) and scattered ecchymotic patches over both shins, forearms, and anterior abdomen; no active mucosal oozing during examination.
- Lymphadenopathy: Generalized, discrete, mobile, rubbery, firm, completely non-tender:
- Bilateral anterior cervical chain: Multiple nodes, largest $1.5 \times 1.0\text{ cm}$.
- Bilateral axillary chain: Multiple nodes, largest $1.5 \times 1.5\text{ cm}$.
- Bilateral inguinal chain: Nodes measuring $1.0 \times 1.0\text{ cm}$.
- Overlying skin is normal, no erythema, warmth, or sinus formation.
- Icterus, Cyanosis, Clubbing, Edema: Absent.
- Oral Cavity: Pale gingiva, small dried blood crust in right anterior nares, no hypertrophic gingival hyperplasia (hypertrophy is characteristic of AML M4/M5, not ALL).
- Sternum & Long Bones: Exquisite tenderness elicited upon gentle thumb pressure over the lower third of the sternum and anterior tibial margins (Sternal tenderness positive).
- Genitalia: Bilateral testes fully descended in scrotum, symmetrical, normal volume (~2 mL), soft, non-tender (no testicular leukemic infiltration).
Systemic Examination
Abdomen
- Inspection: Symmetrically distended, full flanks, umbilicus central; no visible veins, visible pulsations, or scars.
- Palpation: Soft, non-tender; no guarding or rigidity.
- Hepatomegaly: Liver palpable 4.0 cm below right costal margin in midclavicular line, firm, smooth surface, sharp margins, non-tender, total liver span 11.0 cm (normal span for 4y is 7.5 cm).
- Splenomegaly: Spleen palpable 4.5 cm below left costal margin along splenic axis, firm, smooth, non-tender, splenic notch distinctly felt.
- Percussion: Dullness over liver and spleen; no shifting dullness or fluid wave.
- Auscultation: Normal bowel sounds (4-5/min); no hepatic or splenic vascular bruits.
Cardiovascular System
- Precordium: Hyperdynamic impulse; apex beat in 4th intercostal space midclavicular line.
- Auscultation: $S_1, S_2$ normal; Grade 2/6 soft systolic hemic flow murmur heard at left sternal border and pulmonary area (flow murmur secondary to severe anemia). No gallop rhythm or third heart sound.
Respiratory System
- Normal vesicular breath sounds bilaterally; no crepitations, rhonchi, or bronchial breathing.
- Percussion over manubrium sterni: Resonant (no retrosternal dullness; confirms absence of large mediastinal mass).
Central Nervous System
- Alert, conscious, cooperative, GCS 15/15.
- Cranial nerves I to XII intact; pupillary light reflexes brisk and symmetrical.
- Neck supple, Kernig and Brudzinski signs negative.
- Tone normal, power 4+/5 throughout, deep tendon reflexes $2+$ symmetrical, plantars flexor bilaterally.
- Fundus examination: Pale retinal background, no papilledema, no Roth spots or preretinal leukemic infiltrates.
Summary
Master Rohan, a 4-year-old male child born of non-consanguineous parentage, presents with a 4-week history of tri-lineage bone marrow failure (severe pallor, high fever, petechial purpura) accompanied by leukemic skeletal expansion (severe nocturnal bone pain, sternal tenderness) and generalized reticuloendothelial infiltration (generalized rubbery lymphadenopathy, hepatosplenomegaly), in the absence of neurological signs or testicular enlargement.
Final Clinical Diagnosis: Acute Leukemia (most consistent with B-Cell Acute Lymphoblastic Leukemia - ALL), NCI Standard Risk (Age 4 years, initial TLC $<50,000/\mu\text{L}$), presenting with severe anemia, thrombocytopenia, neutropenia, and hepatosplenomegaly, without clinical evidence of overt CNS leukemia, testicular infiltration, or active Tumor Lysis Syndrome.
Differential Diagnosis
| Disorder | Points IN FAVOR | Points AGAINST |
|---|---|---|
| Acute Lymphoblastic Leukemia (ALL) | Peak age 2-5y, triad of pallor, fever, bleeding; severe bone/sternal pain; rubbery generalized lymphadenopathy, hepatosplenomegaly | Primary Diagnosis |
| Acute Myeloid Leukemia (AML) | Marrow failure, pallor, bleeding, hepatosplenomegaly | Less common in 4y (bimodal: neonatal & adolescent); lacks gingival hyperplasia, chloromas (myeloid sarcomas), or skin infiltrates |
| Aplastic Anemia | Severe pancytopenia (pallor, fever, bleeding) | Absence of lymphadenopathy, hepatomegaly, splenomegaly, or bone pain in aplastic anemia (marrow is empty, not packed) |
| Systemic JIA (Still's Disease) | Prolonged fever, joint pain, lymphadenopathy, hepatosplenomegaly | Fever in sJIA is quotidian; rash is salmon-evanescent; sJIA causes reactive thrombocytosis and leukocytosis, NOT pancytopenia or purpura |
| Infectious Mononucleosis (EBV) | Fever, generalized lymphadenopathy, hepatosplenomegaly | Prominent exudative tonsillitis/pharyngitis absent; EBV does not cause severe bone pain or spontaneous petechiae |
| Metastatic Neuroblastoma | Bone pain, pallor, periorbital ecchymosis, cytopenias | Abdominal mass in neuroblastoma is retroperitoneal, nodular, and crosses midline; primary mass absent here |
Investigation Protocol & Diagnostic Workup
flowchart TD
    A["Child with Triad of Marrow Failure (Pallor, Fever, Petechiae) & Bone Pain"] --> B["CBC with Peripheral Blood Smear & Reticulocyte Count"]
    B --> C{"Peripheral Blasts Observed?"}
    C -->|Yes / High Suspicion| D["Bone Marrow Aspiration & Biopsy (Morphology, Cytochemistry, Flow Cytometry)"]
    D --> E["Flow Cytometry: CD19+, CD10+, CD22+, cCD79a+ (B-ALL) vs CD3+, CD7+ (T-ALL)"]
    E --> F["Cytogenetics & FISH: ETV6-RUNX1, BCR-ABL1, KMT2A, TCF3-PBX1, Hyperdiploidy"]
    F --> G["Diagnostic Lumbar Puncture: CSF Cytocentrifugation (CNS-1, CNS-2, CNS-3)"]
    G --> H["Metabolic TLS Panel: Uric Acid, K+, Phosphorus, Calcium, LDH, Creatinine"]
    H --> I{"Laboratory / Clinical TLS?"}
    I -->|Yes| J["Hyperhydration 3000 mL/m²/day + Rasburicase 0.2 mg/kg IV"]
    I -->|No| K["Hyperhydration + Allopurinol Prophylaxis"]
    K --> L["Initiate Multi-Agent Induction Chemotherapy (BFM / ICMR Protocol)"]
1. Hematological Evaluation
- Complete Blood Count (CBC):
- Hemoglobin: $5.4\text{ g/dL}$ (Severe normocytic normochromic anemia; reference $11.5-13.5\text{ g/dL}$).
- Total Leukocyte Count (TLC): $22,400/\mu\text{L}$ (Elevated; blasts present; reference $5,000-12,000/\mu\text{L}$).
- Absolute Neutrophil Count (ANC): $380/\mu\text{L}$ (Severe neutropenia, $<500/\mu\text{L}$).
- Platelet Count: $18,000/\mu\text{L}$ (Severe thrombocytopenia, $<20,000/\mu\text{L}$; reference $150,000-450,000/\mu\text{L}$).
- Peripheral Blood Smear (PBS):
- Marked anisopoikilocytosis, severe normocytic normochromic anemia.
- White blood cells show $65\%$ circulating lymphoblasts: small to medium cells, high nuclear-to-cytoplasmic (N:C) ratio, condensed chromatin, indistinct nucleoli, and scanty agranular basophilic cytoplasm (FAB L1 morphology).
- Normal myeloid and erythroid precursors markedly depressed; platelets severely reduced.
2. Bone Marrow Aspiration & Biopsy (Definitive Gold Standard)
- Morphology: Hypercellular marrow ($>95\%$ cellularity) with complete effacement of normal hematopoiesis by $88\%$ lymphoblasts.
- Cytochemistry: Myeloperoxidase (MPO) negative; Periodic Acid-Schiff (PAS) block positivity positive; Non-specific esterase (NSE) negative.
- Multiparametric Flow Cytometry (Immunophenotyping):
- Gated blasts are strongly positive for B-cell lineage markers: CD19 ($98\%$), CD10 / CALLA ($94\%$), CD22 ($92\%$), and cytoplasmic CD79a ($96\%$).
- Negative for T-cell markers (CD3, CD5, CD7) and myeloid markers (MPO, CD13, CD33).
- Diagnostic Conclusion: Common B-Cell Acute Lymphoblastic Leukemia (Pre-B ALL).
3. Cytogenetics and Molecular Diagnostics
- Ploidy & Karyotype: Hyperdiploidy ($>50$ chromosomes; associated with favorable prognosis).
- FISH & RT-PCR Translocation Panel:
- $t(12;21)(p13;q22)$ encoding $ETV6\text{-}RUNX1$ (TEL-AML1): Positive (Favorable prognostic factor).
- $t(9;22)$ ($BCR\text{-}ABL1$ / Philadelphia chromosome): Negative.
- $KMT2A$ ($11q23$ / MLL gene rearrangement): Negative.
- $t(1;19)$ ($TCF3\text{-}PBX1$): Negative.
4. Baseline Tumor Lysis Syndrome (TLS) & Biochemical Profile
- Serum Uric Acid: $5.8\text{ mg/dL}$ (Normal $<6.5\text{ mg/dL}$).
- Serum Potassium: $4.4\text{ mEq/L}$ (Normal $3.5-5.0\text{ mEq/L}$).
- Serum Phosphorus: $4.8\text{ mg/dL}$ (Normal $3.5-5.5\text{ mg/dL}$).
- Serum Calcium: $9.2\text{ mg/dL}$ (Normal $8.5-10.2\text{ mg/dL}$).
- Serum LDH: $1420\text{ U/L}$ (Markedly elevated; reflects high leukemic cell turnover; normal $<250\text{ U/L}$).
- Serum Creatinine: $0.4\text{ mg/dL}$; Blood Urea: $22\text{ mg/dL}$.
- Liver Function Tests: AST $42\text{ U/L}$, ALT $36\text{ U/L}$, Total Bilirubin $0.8\text{ mg/dL}$.
5. Extramedullary Staging & Imaging
- Diagnostic Lumbar Puncture (CSF Analysis):
- Opening pressure normal; CSF clear.
- Total cells: $2\text{ cells}/\mu\text{L}$; Protein $22\text{ mg/dL}$, Glucose $58\text{ mg/dL}$.
- CSF Cytocentrifugation: No leukemic blasts observed $\to$ Classified as CNS-1 Status (Non-CNS leukemia).
- Chest Radiograph (Erect AP):
- Normal cardiothoracic ratio; no anterior mediastinal widening or mass (rules out T-ALL mediastinal compression).
- Abdominal Ultrasound:
- Hepatosplenomegaly with homogenous parenchyma; kidneys normal size without nephromegaly or chloromas.
Comprehensive Multi-Phase Management Plan
flowchart LR
    A["Phase 1: Pre-Phase & TLS Prophylaxis (Days 1-7)"] --> B["Phase 2: Induction Chemotherapy (Days 8-35)"]
    B --> C["Phase 3: Consolidation / Intensification (Months 2-3)"]
    C --> D["Phase 4: Re-Induction / Delayed Intensification (Months 4-5)"]
    D --> E["Phase 5: Maintenance Chemotherapy (Total 2-2.5 Years)"]
1. Emergency Pre-Phase & Supportive Care
- Airway & Hemodynamics: Child placed in a positive-pressure HEPA-filtered protective isolation room.
- Tumor Lysis Syndrome Prophylaxis:
- Hyperhydration: Infuse IV fluids at $3000\text{ mL/m}^2/\text{day}$ ($125\text{ mL/m}^2/\text{hour}$) using $0.45\% \text{ NaCl in } 5\% \text{ Dextrose}$ with zero potassium.
- Maintain urine output $>100\text{ mL/m}^2/\text{hour}$ (specific gravity $<1.010$).
- Xanthine Oxidase Inhibition: Oral Allopurinol $300\text{ mg/m}^2/\text{day}$ divided q8h. (Rasburicase reserved if uric acid rises $>8\text{ mg/dL}$).
- Blood Component Therapy:
- Transfuse Leukodepleted, Irradiated Packed Red Blood Cells (PRBC) at $10\text{ mL/kg}$ slowly over 4 hours (target $\text{Hb} > 7.0-8.0\text{ g/dL}$).
- Transfuse Single Donor Platelets (SDP) to elevate platelet count $>20,000/\mu\text{L}$ before diagnostic bone marrow or lumbar puncture.
- Febrile Neutropenia Protocol: Stat blood cultures drawn from two sites; empirical IV Piperacillin-Tazobactam ($300\text{ mg/kg/day}$ divided q6h) initiated within 60 minutes.
2. Multi-Agent Induction Chemotherapy (ICMR / BFM Protocol)
- Steroid Prophase (Days 1–7): Oral Prednisolone ($60\text{ mg/m}^2/\text{day}$) to evaluate in vivo steroid response:
- Good Prednisolone Responder (PGR): Absolute blast count in peripheral blood on Day 8 is $<1,000/\mu\text{L}$.
- Three-Drug Induction for NCI Standard Risk (Days 8–35):
- Prednisolone: $60\text{ mg/m}^2/\text{day}$ orally in 3 divided doses from Day 8 to Day 28, then tapered over 7 days.
- Vincristine: $1.5\text{ mg/m}^2$ IV bolus weekly on Days 8, 15, 22, and 29 (capped at maximum $2.0\text{ mg}$).
- L-Asparaginase (or PEG-Asparaginase): $5,000\text{ IU/m}^2$ IM/IV every 3 days for 8 doses (or Pegaspargase $2,500\text{ IU/m}^2$ on Day 12).
- CNS Prophylaxis: Age-adjusted Intrathecal Triple Therapy (TIT): Methotrexate ($12\text{ mg}$) + Cytarabine ($30\text{ mg}$) + Hydrocortisone ($15\text{ mg}$) administered on Days 1, 15, and 29.
3. End-of-Induction Assessment & Minimal Residual Disease (MRD)
- Day 33 Bone Marrow Aspiration:
- Morphological Remission: Marrow blasts $<5\%$ ($M1$ status).
- Minimal Residual Disease (MRD) by 8-Color Flow Cytometry:
- If $\text{MRD} < 0.01\%$ ($<10^{-4}$): Patient continues on Standard Risk Consolidation and Maintenance ($>90\%$ cure rate).
- If $\text{MRD} \ge 0.01\%$: Re-stratify immediately to High Risk; intensify with High-Risk blocks, Blinatumomab, or evaluate for Allogeneic HSCT.
4. Consolidation, Maintenance & Long-Term Surveillance
- Consolidation: High-Dose Methotrexate ($2.0\text{ to } 5.0\text{ g/m}^2$ IV 24-hour infusion) with Leucovorin rescue + 6-Mercaptopurine ($50\text{ mg/m}^2/\text{day}$).
- Maintenance Therapy: Daily oral 6-Mercaptopurine ($50\text{ mg/m}^2$) + Weekly oral Methotrexate ($20\text{ mg/m}^2$) with monthly pulses of Vincristine and Dexamethasone, continued for total 2 years from diagnosis in girls and 2 to 2.5 years in boys.
- Infection Prophylaxis: Oral Co-trimoxazole ($5\text{ mg/kg/day}$ TMP component) twice weekly on consecutive days to prevent Pneumocystis jirovecii pneumonia (PJP).