
Anatomy And Physiology
Horizontal Gaze Pathway
- Voluntary conjugate horizontal eye movements begin in the posterior inferior part of the frontal lobe cortex.
- The pathway runs downwards to the pontine tegmentum.
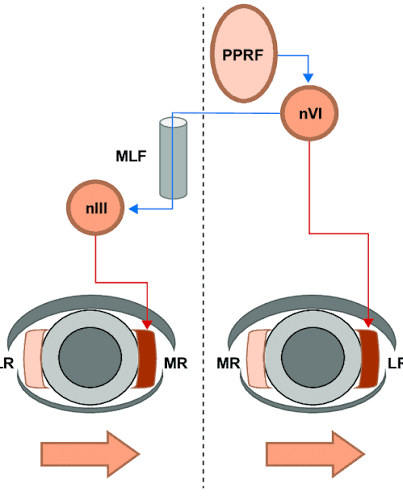
- These cortical fibers terminate in the contralateral paramedian pontine reticular formation (PPRF).
- The PPRF connects to the ipsilateral sixth cranial nerve nucleus.
- The medial longitudinal fasciculus (MLF) connects the PPRF to the third and sixth nerve nuclei to coordinate simultaneous abduction and adduction.
- Therefore, the right frontal lobe center mediates lateral gaze to the left side, and vice versa.
Vertical Gaze Pathway
- Pathways for vertical eye movements arise diffusely from the parieto-temporal and occipital cortices.
- These fibers project to the midbrain reticular formation.
- The pathway governing upward eye movements runs dorsal to the pathway for downward eye movements.
Assessment From History
- Elicit a history of double vision (diplopia).
- Ask about difficulty tracking or following fast-moving objects.
- Inquire if the child's eyes seem stuck or deviated to one particular side.
- Elicit a history of abnormal head posturing or head tilting, which may indicate compensation for a gaze palsy.
- Ask about any recent infections, trauma, or signs of raised intracranial pressure.
Clinical Examination
Inspection
- Observe the spontaneous resting position of the eyeballs.
- Look for conjugate lateral deviation of the eyes.
- Observe if the eyes roll upward continuously or have downward conjugate deviation (ocular bobbing).
- Look for spontaneous nystagmus and note its direction.
Palpation
- Palpation is not applicable.
Percussion
- Percussion is not applicable.
Auscultation
- Auscultation is not applicable.
Testing Procedure
Conjugate Gaze Testing
- Fix the position of the child's head.
- Ask the child not to move the head while moving the eyes.
- Ask the child to follow a target (like a bright toy or your finger).
- Move the finger to form an English letter 'H' to test all extraocular muscles and conjugate gaze in horizontal and vertical planes.
- Note any restriction of movement, failure of both eyes to move together, or nystagmus.
Oculomotor Apraxia Testing
- Instruct the child to keep their head still or have the parents hold the head.
- Keep your hands wide apart and flicker your fingers on one side, then the other.
- Instruct the child to look immediately at the flickering fingers.
- Observe for saccadic movements.
- In oculomotor apraxia, the child will lack saccadic pursuit and instead thrust the head to follow the object, while the eyes lag behind.
Interpretation Of Lesions
Cortical Lesions
- Interruption of the cortical efferent pathway above the decussation results in eye deviation.
- A destructive frontal lobe lesion causes the eyes to deviate towards the same side as the lesion.
- An irritative frontal lesion (like a focal seizure) causes tonic deviation of the eyes to the opposite side.
Brainstem Lesions
- A destructive pontine lesion (involving the PPRF) leads to gaze deviation towards the opposite side.
- Lateral gaze palsy can signify central herniation with compression.
- Tonic upward gaze indicates bilateral hemispheric damage.
- Ocular bobbing (rapid downward jerk followed by a slow return) indicates a pontine lesion.
Internuclear Ophthalmoplegia (INO)
- Results from interruption of the medial longitudinal fasciculus (MLF).
- During horizontal gaze, the child cannot adduct the eye on the ipsilateral side of the lesion.
- The contralateral abducting eye will develop nystagmus.
One And A Half Syndrome
- Results from interruption of both the MLF and PPRF on one side.
- Causes complete gaze palsy on the affected side.
- Also causes loss of adduction of the ipsilateral eye when looking to the opposite side.
- The only horizontal movement remaining is abduction of the contralateral eye.
Age-Specific Key Points
Infants And Comatose Children
- Use the Doll's eye maneuver (oculocephalic reflex) to test brainstem integrity.
- Ensure there is no cervical spine injury before performing the maneuver.
- Turn the head rapidly side-to-side or vertically.
- A normal response (positive) is conjugate deviation of the eyes in the direction opposite to the head movement.
- Absent response indicates structural brainstem abnormalities or metabolic-toxic encephalopathy.
Example For EXAM
Gaze Assessment:
- Inspection: Eyes are centrally placed in the primary position of gaze. No resting tonic deviation of eyes noted. No spontaneous nystagmus or ocular bobbing observed.
- Conjugate Movements: Full range of conjugate horizontal and vertical eye movements is present. The child is able to smoothly track objects in all cardinal directions without breaking conjugate alignment.
- Saccades: Saccadic pursuit movements are intact and brisk bilaterally. No compensatory head thrusting required (oculomotor apraxia negative).
- Specific Maneuvers: No adduction deficit or abducting nystagmus noted on lateral gaze (Internuclear ophthalmoplegia negative).
- Interpretation: Supranuclear, nuclear, and internuclear pathways for horizontal and vertical conjugate gaze are intact and functioning normally.